As the popularity of GLP-1-based drugs soars for weight loss, Rozalina McCoy discusses the medications’ most effective uses, how they differ from related SGLT-2s, and the need to balance their potential risks and rewards.

Losing weight, and keeping it off, can be hard. But these days, GLP-1 (glucagon-like peptide-1) medications are a popular choice for shedding those stubborn pounds. According to a 2026 Gallup poll, the number of adults in the United States taking GLP-1s to lose weight has quadrupled since 2024 to 11% of the population.
Approved in 2005 to lower blood sugar in adults with type 2 diabetes, GLP-1s are highly effective for that intended purpose and offer other clinical benefits, but their growing off-label uses and long-term implications aren’t well understood, particularly among people without type 2 diabetes and other high-risk conditions who were the focus of GLP-1 clinical trials.
Rozalina McCoy, director of the Center for Population Health at the University of Maryland Institute for Health Computing (UM-IHC) and an associate professor of medicine at the University of Maryland School of Medicine, co-authored a paper in the September 2026 issue of the journal Diabetes Research and Clinical Practice that associated GLP-1 use with an increased risk of non-obesity-related cancers. She has also published multiple studies demonstrating the benefits of GLP-1 medications for preventing heart disease and kidney disease complications in people with type 2 diabetes and explored via social media the experience of individuals taking GLP-1 medications.
In this Q&A, McCoy discusses both the exciting benefits of GLP-1-type therapies and the concerning unknowns about their increasingly casual use.
This interview has been edited for length and clarity.
How did you become interested in studying GLP-1 therapies, and what is the focus of your research?
I’ve been studying the management of diabetes since 2009, when I started my residency. That was still the “glucose-centric era”—when lowering blood sugar was the primary goal of treating diabetes. But lowering blood sugar has its own risks for many patients, especially if we lower it too much or need to use many medications to do it—each with their own risks and benefits. Ultimately, the A1C (a measure of average blood sugar over approximately three months) is just a number. I believe it is most important to focus on what matters most to patients: improving health, functional status and well-being—not just changing their lab results.
With that in mind, the fact that GLP-1s and drugs called SGLT-2 (sodium-glucose cotransporter 2) inhibitors, which can complement GLP-1s but work on separate pathways in the body, not only lower blood sugar levels but more importantly have added benefits including kidney, cardiovascular and metabolic protection makes them very interesting to me.
My focus is primarily on type 2 diabetes, and part of my work has been comparing these treatments to one another and to other therapies with the goal of understanding which patients benefit the most from their use and the impacts of treatment across the wide range of people living with type 2 diabetes. SGLT-2s work in part by preventing the kidneys from reabsorbing sugar and have slightly different health benefits from GLP-1s, including superior kidney protection and heart failure benefits. GLP-1s provide higher weight loss and improvement in metabolic liver disease and seem to offer greater protection against stroke. All these benefits, for both medication classes, are seen irrespective of blood sugar reduction.
I’m currently gathering information from social media—specifically Facebook and Reddit—to help us understand why people take these medications, how they feel about them, what side effects they experience and more.
What are some additional positive outcomes associated with these medications?
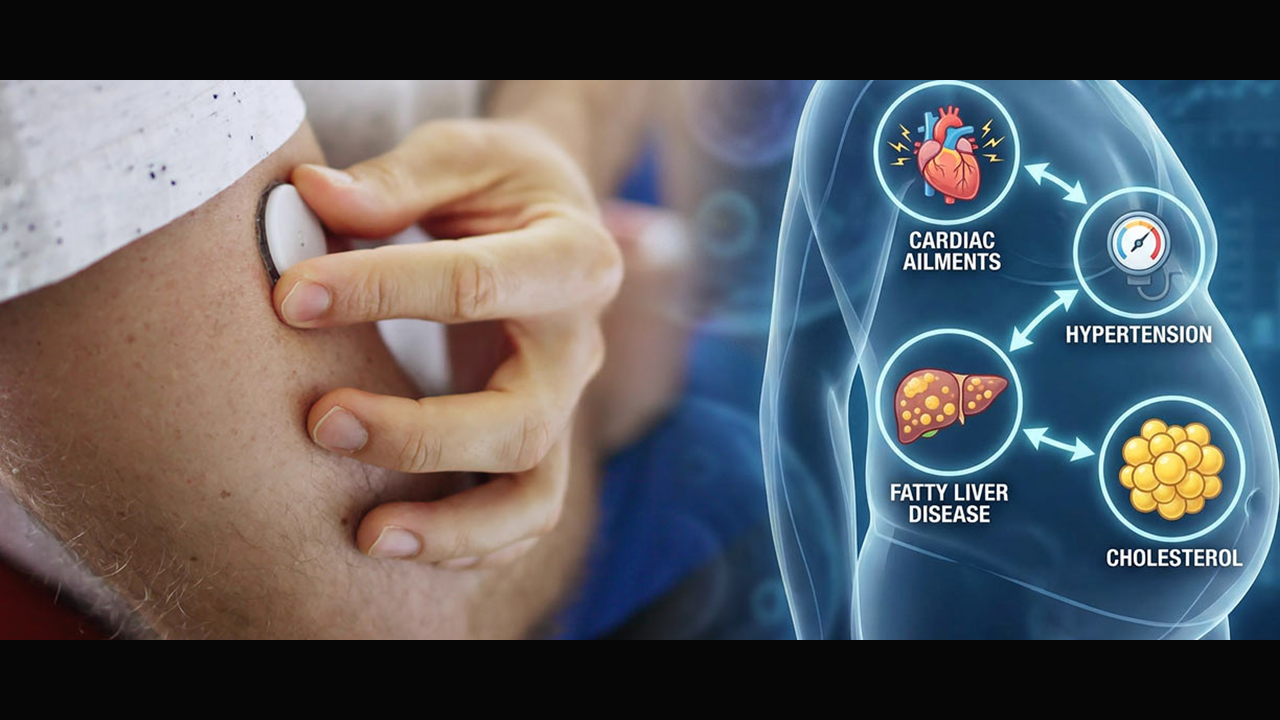
For patients with and without diabetes, it’s clear the medications can reduce weight significantly. They improve metabolic dysfunction related to liver disease. There is a real mortality benefit for people with diabetes and with cardiovascular disease, plus improvements in obesity-related complications like sleep apnea and arthritis. Our team has looked at cardiovascular outcomes, kidney outcomes, eye health and amputations in type 2 diabetes and found GLP-1s and SGLT-2s are both better than alternative treatments such as sulfonylureas. We’re now comparing these two therapies to metabolic surgery for obesity as well.
Notably, we’ve noticed a “treatment benefit paradox,” which means patients who are most likely to benefit from a particular treatment are often less likely to get it than patients less likely to benefit. Patients with heart disease and kidney disease, for example, have not been getting GLP-1s and SGLT-2s as often as they should. It raises questions about accessibility, affordability and insurance that we’re trying to answer. We’ve also found that physicians across specialties who have less knowledge and training about these types of drugs are less likely to prescribe them.
Tell us about your recent study looking at non-obesity-related cancers in patients with diabetes.
There has been a lot of interest in whether GLP-1s can reduce cancer risk, since obesity is a major risk factor for many cancers and GLP-1s are the most effective medications for weight loss we have. In studies that focused only on obesity-related cancers, GLP-1s were generally associated with lower risk of many, though not all, of these cancers compared to other diabetes medications, most notably insulin. We wanted to compare GLP-1s to other beneficial drugs like SGLT-2s—comparing apples to apples in a way—and to examine cancers that are not associated with obesity. And there was the surprise: In our study we found that in patients being treated for type 2 diabetes, GLP-1s were associated with increased risk of non-obesity-related cancers compared with other drug treatments.
We redid this analysis multiple times, considering all kinds of potentially confounding factors, like screening and accessibility differences, but the result was consistent, and it cut very cleanly along obesity- and non-obesity-related cancer lines.
This was not a randomized controlled trial, so we can’t say definitively that GLP-1s are the cause. But we’ve accounted for everything we could think of—as much as was feasible with the data that we had—that might affect the results. We don’t know why the risk increases and need to further investigate it. But an important takeaway is that you really shouldn’t take any medication you don’t need. Using GLP-1s just to lose a little weight if you don’t have diabetes or heart disease or significant obesity or other complications that the drugs are shown to improve is an unnecessary potential risk.
Another take-home message: If you are taking one of these medications and have a worrisome symptom, don’t ignore it—get evaluated.
Do we know the long-term effects of GLP-1s?
That continues to be a big question. Most studies come from outside the United States, where there is more complete capture of entire populations over time. These studies have shown that for patients prescribed these medications because they are at high risk for heart disease, the benefits clearly outweigh the risks. In the U.S., long-term studies are more challenging because we don’t have a database covering all Americans and there are affordability and insurance coverage barriers to long-term use, so many patients stop treatment within a year, challenging long-term analyses.
These drugs are no longer new, having now been around for more than two decades. What is new is who is using them and the potency of the newer drugs being used. For GLP-1s, the clinical trials have focused on patients with diabetes with high cardiovascular disease risk, or obesity and high cardiovascular disease risk, or obesity and sleep apnea, or obesity and arthritis. You can see the pattern. Many of the participants in these trials are middle-aged or older. And yet, in the real world, many people taking these drugs are young, not diagnosed with significant obesity or obesity at all, and without heart disease or other obesity-related conditions. The benefit-risk calculation in such individuals is very different than what we’ve seen in clinical trials. And most worrisome is that with greater use of compounded products, we increasingly don’t know where people might be getting the meds, what is actually in the products they are taking and what doses they’re taking. So, we simply don’t have the information we need to assess long-term effects.
What message do you want readers to take away from this conversation?
I don’t want to create worry or confusion around GLP-1s—these are very important, clinically transformative and useful medications that are helping improve and save lives. But like all medications, they should not be used without a good reason. Though highly effective for a wide range of cardiometabolic conditions, no medication is without potential risks, so it is important to understand where the balance of benefit and risk falls for each patient given their specific needs.
There are also many unknowns: We haven’t studied GLP-1s in every age group or in people without obesity-related health problems. Yet I hear many young people seeking out GLP-1s to lose weight when they don’t have significant obesity or health problems that are likely to be improved with treatment. I’m concerned about people getting them from spas, gyms, off the web and elsewhere, raising concerns about dosing, purity and safety. Then we have concerning findings like ours related to non-obesity-related cancers that need to be further explored. It is one thing to take GLP-1s when there is a clear benefit but a completely different story if the benefit of treatment is likely much lower.
I worry about the future if we aren’t smart and intentional about how we use these therapeutics—we should be fully weighing benefits against risks and unknowns. They are remarkably useful drugs but not a magic solution to every problem without consequence.
###
This article is for informational purposes only and does not replace professional medical advice. Always consult a licensed healthcare provider for concerns about your health.